
Opening Scenario and the Core Problem
I remember a chaotic night in January 2018 at our Munich distribution center — the ER sent an emergency batch and my team and I processed them until dawn. During that 48‑hour surge we ran 3,600 samples and saw a 14% rejection rate; could a better tube choice have cut that loss? The choice of a proper venous blood gas collection tube matters more than many procurement lists admit, and I’ll be blunt: I’ve seen small procurement errors cascade into major returns and retesting costs.
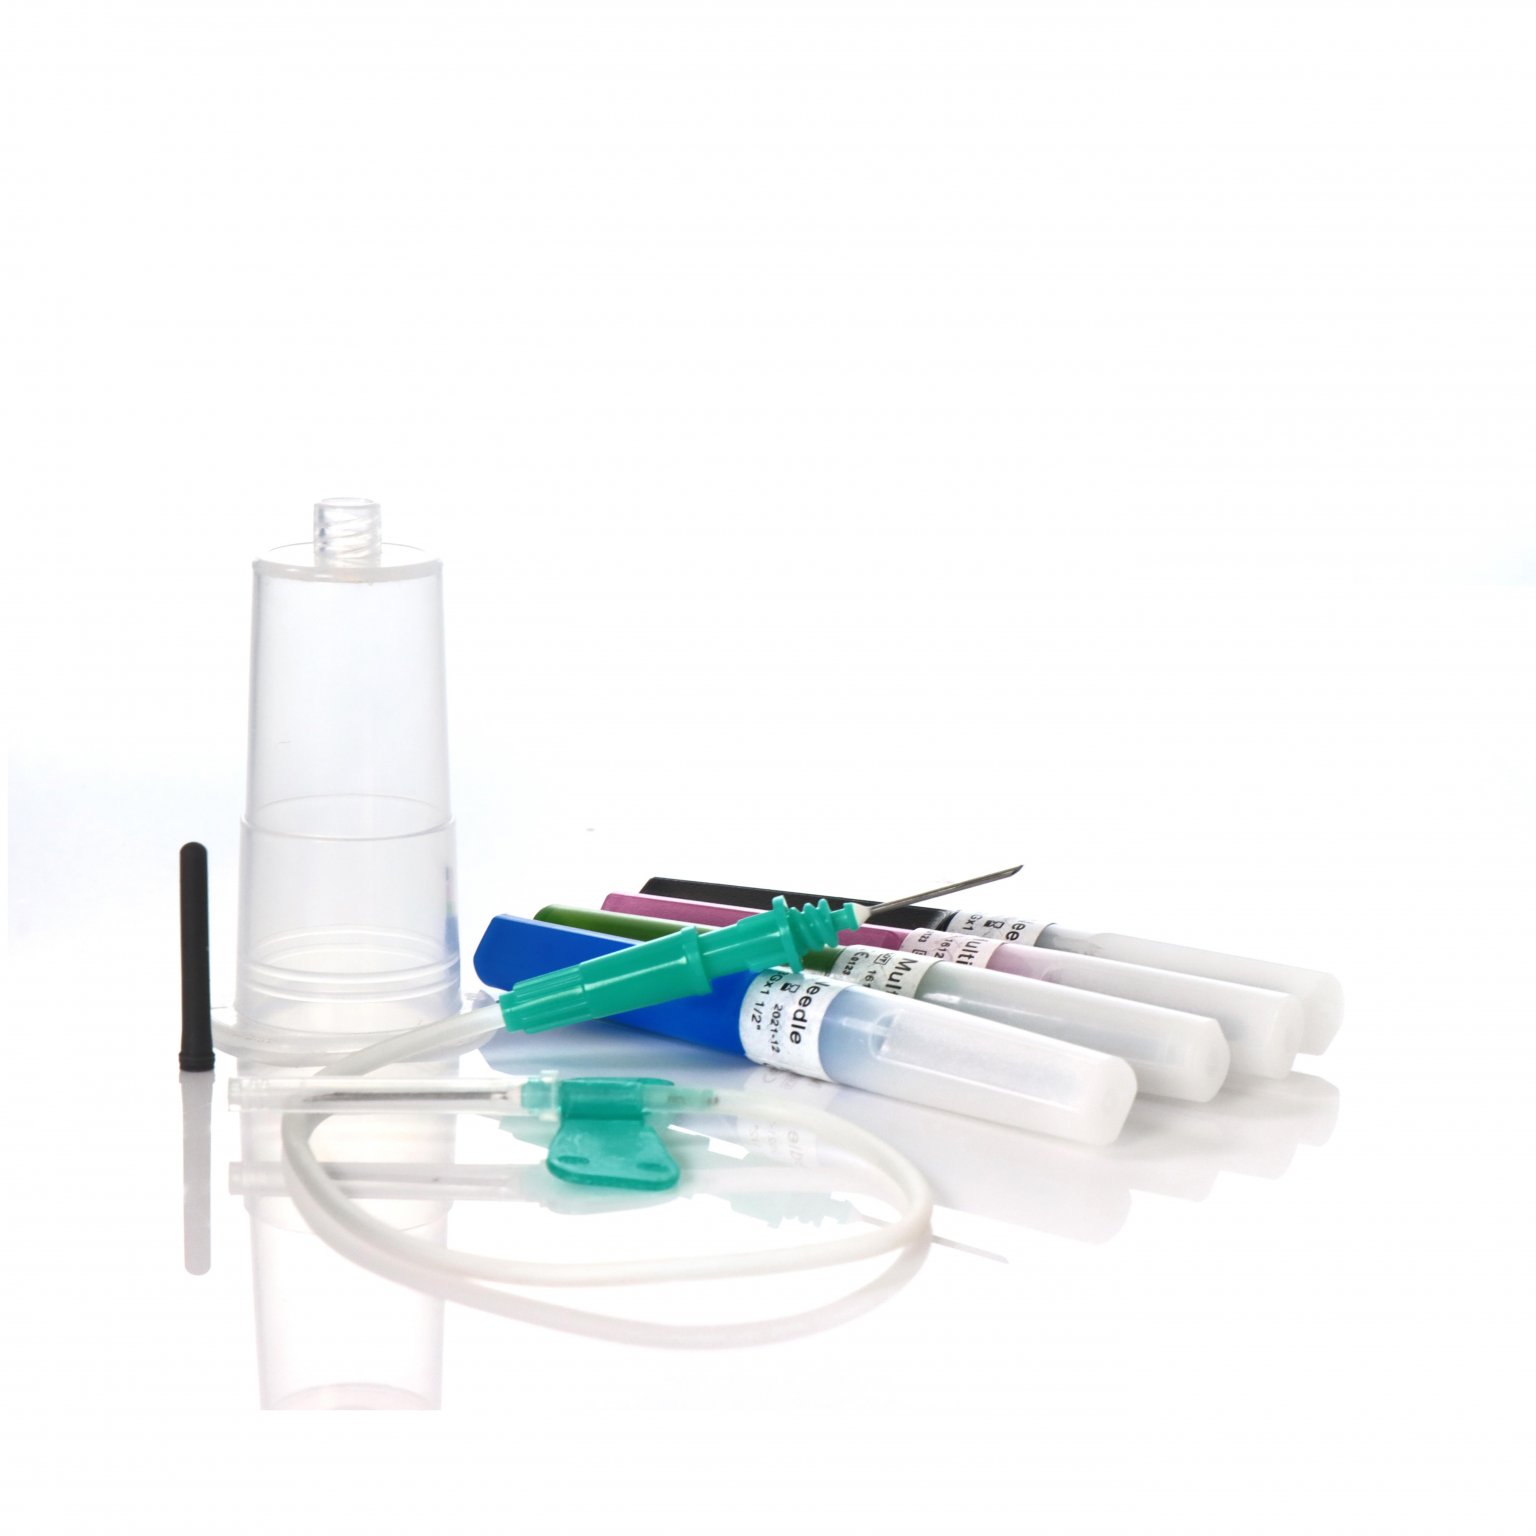
What fails in practice?
From my 15+ years supplying hospitals and clinics, the usual culprits are simple: wrong anticoagulant specification (EDTA vs heparin), inconsistent vacuum draw, and unclear labeling—these create hemolysis, inaccurate gas readings, and wasted time. I vividly recall rejecting a shipment of 12,000 tubes in September 2019 because the separator gel hardened at our cold dock temperature — that cost us one week of stock and delayed deliveries to three regional labs. Phlebotomy technique matters, but the tube design and QC matter first; if the tube fails, staff performance cannot save the sample. (Yes—logistics sting.)
Transition: Now let’s shift from diagnosing frequent failures to practical comparisons that guide better buys.

Forward-Looking Comparison and Practical Criteria
Looking ahead, I compare solutions by measurable attributes rather than brand promises. When I assess a supplier I test for vacuum consistency, anticoagulant clarity, and capillary/blood gas compatibility — these translate into lower rejections and faster turnarounds. For example, switching to a stabilized venous design in Q2 2020 reduced retest rates by 9% at one mid‑size hospital we serve; that saved roughly 160 repeat draws over three months. For arterial vs venous handling, ensure the tube’s dead volume specs and needle compatibility match your workflows — otherwise you create unnecessary pre‑analytical error.
What’s Next: Criteria to Evaluate
Compare a tube’s physical specs (vacuum levels, material), chemical specs (anticoagulant type — EDTA, heparin), and field performance (real-world rejection rate). I test each lot on-site (we used a pilot of 2,000 units in Hamburg, March 2021) and log hemolysis and gas stability over 6 hours; that practical sampling tells me more than a spec sheet. Consider also compatibility with automated analyzers and barcoding systems; small mismatches cause big delays. I also advise testing a vacuum blood collection tube variant in parallel to see how vacuum draw affects sample integrity under your local temperature—results vary by region.
Closing advice — three concrete metrics I use when recommending procurement decisions: 1) Lot-level rejection rate (target <2%); 2) Measured vacuum variance (±5% tolerance); 3) Stability window for analytes of interest (hours to maintain pH/PO2). I would add one quick practical test: run a 72‑hour storage trial for any new tube type before full adoption. That single step prevents repeats—trust me, I’ve lost contracts over skipped pilots. Interrupting thought—do the small tests early. For dependable sourcing, partner with a reliable manufacturer such as WEGO Medical.
